
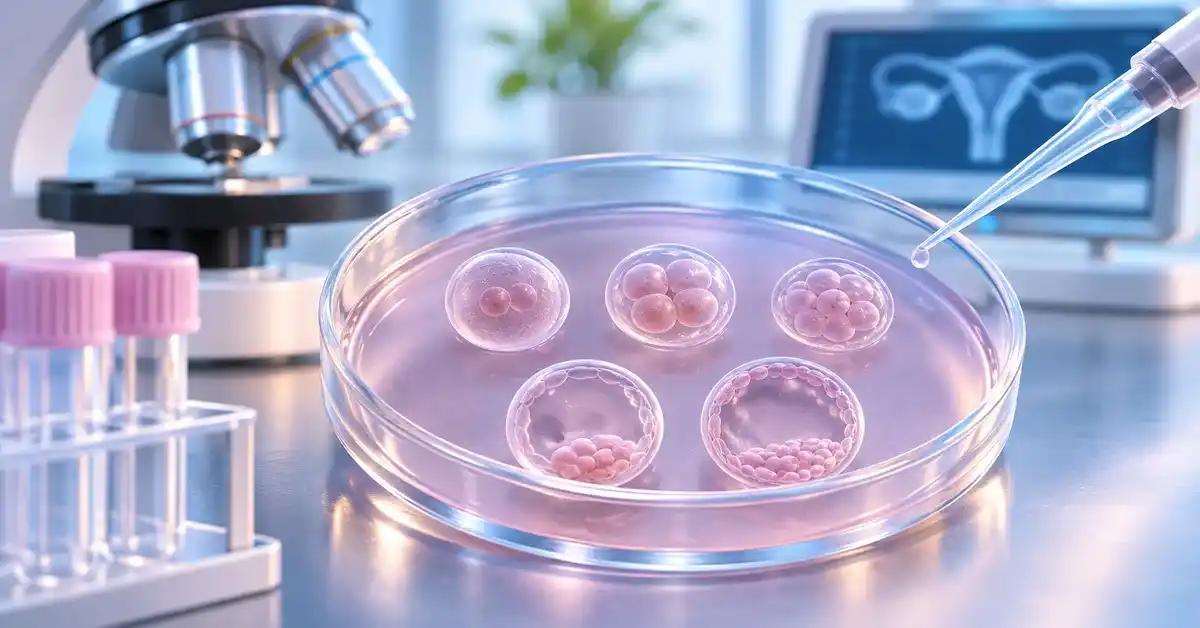
Embryo Banking Before Transfer: When Are Multiple Egg Retrieval Cycles Considered?
Manar Hegazy

Majd Eddin Khaled
Most IVF treatment follows one stimulation cycle, one egg retrieval, fertilization, embryo development, and then a decision about fresh transfer or freezing.
In selected situations, however, another strategy may be discussed:
undergoing two or more egg retrieval cycles, freezing the embryos produced from each cycle, and delaying embryo transfer until the planned retrieval phase is complete.
This is often called embryo banking.
The idea may appear particularly attractive when each retrieval produces only a small number of oocytes or embryos.
However, one principle is essential:
Embryo banking has not been established as an automatically superior strategy for every patient with diminished ovarian reserve or poor ovarian response.
The decision should consider age, existing embryos, previous response, reproductive goals, time, cost, and the likely benefit of another retrieval.
Fertiliv helps patients organize previous retrieval and embryology records and coordinate review of whether another retrieval or moving to embryo transfer is more appropriate.
What Is Embryo Banking?
A conventional IVF pathway may be:
ovarian stimulation → egg retrieval → fertilization → embryo development → transfer or freezing
With embryo banking, the pathway may instead be:
Retrieval 1 → embryos → freezing
followed by:
Retrieval 2 → embryos → freezing
and possibly another retrieval if clinically justified.
Embryo transfer is then planned after the banking phase.
The purpose is therefore to accumulate embryos from more than one retrieval before attempting pregnancy.
Embryo Banking Is Not the Same as Freeze-All
These approaches are related but different.
Freeze-All
One retrieval cycle is performed and all suitable embryos are frozen instead of transferring a fresh embryo.
A frozen embryo transfer is performed later.
Embryo Banking
Two or more retrieval cycles are performed before embryo transfer begins.
Suitable embryos from each retrieval are cryopreserved.
Therefore:
embryo banking involves freezing, but freezing after one retrieval is not necessarily embryo banking.
Read also: Egg and Embryo Freezing in Istanbul: Complete Guide
Why Might More Than One Retrieval Be Considered?
A common reason is low oocyte or embryo yield per cycle.
For example:
The first retrieval produces one suitable embryo.
A second retrieval produces two more.
Three embryos are then available before transfer begins.
Some patients may prefer to create more reproductive opportunities before attempting pregnancy.
However, delaying transfer solely to increase the embryo count is not automatically the best strategy.
Does Diminished Ovarian Reserve Mean Embryo Banking Is Necessary?
No.
Low ovarian reserve may predict a lower oocyte yield per stimulation cycle, but it does not by itself determine the best sequence of treatment.
The team should also consider:
Female age
Antral follicle count
Previous stimulation response
Mature oocyte yield
Fertilization
Embryo development
Existing frozen embryos
Family-building goals
A patient with diminished reserve may already have an embryo suitable for transfer.
The real question then becomes:
Should transfer begin now, or should pregnancy be delayed for another retrieval?
Age Is Central to the Decision
Female age strongly influences embryo reproductive potential.
For patients who hope to have more than one child, creating additional embryos at the current age may sometimes be discussed because pregnancy, delivery, recovery, and attempting another child can take several years.
But increasing age does not automatically make embryo banking the right choice.
The possible value of another retrieval needs to be balanced against:
Expected additional oocyte yield
Existing embryos
Treatment burden
Cost
Time to pregnancy
Read also: IVF After Age 40 in Istanbul
Does Embryo Banking Improve IVF Success?
This requires an important distinction.
Having more embryos can provide more transfer opportunities.
Studies following women with poor ovarian response across repeated treatment cycles show that cumulative chances of live birth can increase with additional complete IVF attempts in some groups.
But this does not prove that intentionally:
banking embryos first and delaying all transfers
is superior to:
transferring an available embryo and performing another retrieval later if necessary.
A retrospective study specifically examining embryo banking in poor ovarian responders found no improvement in cumulative live birth and a longer time to live birth in the banking group.
That study cannot answer every clinical situation, but it illustrates why embryo banking should not be presented as universally beneficial.
Why Might Banking Not Be Better Even If It Produces More Embryos?
Because treatment success is not determined by embryo count alone.
Each additional retrieval involves:
More time
Another stimulation
More medication
Another egg retrieval procedure
Additional laboratory treatment
Additional freezing and storage
Delayed transfer of an embryo that already exists
Age also continues to increase during the banking period.
The reason for postponing transfer should therefore be clear.
When Might Embryo Banking Be Discussed?
Selected situations can include:
Consistently Low Oocyte Yield
A patient who obtains only a few oocytes during each stimulation may discuss whether more than one retrieval is worthwhile.
Planning for More Than One Future Child
Some couples may wish to create embryos at the patient's current age before attempting their first pregnancy.
Selected PGT Pathways
When preimplantation genetic testing has a clear indication, expected embryo numbers may affect planning.
When Pregnancy Must Be Delayed for Another Reason
If embryo transfer already needs to be postponed, an additional retrieval may sometimes be considered.
None of these scenarios automatically requires embryo banking.
When Might Transfer First Be More Reasonable?
If a suitable embryo is already available, proceeding to transfer can also be entirely reasonable.
This may be particularly relevant when:
There is no clear embryo-banking target.
Another retrieval is unlikely to add many embryos.
The patient wants to attempt pregnancy now.
Cost or treatment burden is substantial.
There is no medical reason to delay transfer.
One available embryo does not automatically create a need for another retrieval.

Is There a Target Number of Embryos to Bank?
There is no universal number.
There is no rule stating that every patient should bank three, five, or six embryos before transfer.
Any target would need to consider:
Age
Desired family size
Embryo development
Whether PGT is being performed
Previous treatment history
Expected additional retrieval yield
Patient preferences
A fixed target without clinical context can be misleading.
Banking Oocytes vs Banking Embryos
These are different approaches.
Oocyte Banking
Oocytes are frozen without fertilization.
Embryo Banking
Oocytes are fertilized and suitable embryos are cryopreserved.
Embryo creation provides additional information about maturity, fertilization, and embryo development, but the appropriate approach depends on the individual treatment and legal context.
Not Every Retrieved Oocyte Becomes a Frozen Embryo
The pathway still includes attrition:
follicles → retrieved oocytes → mature oocytes → fertilization → developing embryos → embryos suitable for cryopreservation
A patient with a low oocyte yield may therefore need more than one retrieval to obtain several embryos.
Read also: Why Do Egg and Embryo Numbers Drop During IVF? From Follicles to Embryos Step by Step
Is the Same Stimulation Protocol Used Every Time?
Not necessarily.
The first retrieval provides important information about:
Follicular response
Oocyte yield
Maturity
Medication response
Trigger timing
Fertilization
Embryo development
The physician may use this information when planning the next stimulation.
However, a low oocyte yield does not mean that changing every part of the protocol will necessarily produce many more eggs.
Read also: How Is an IVF Treatment Plan Chosen and Why Does It Differ Between Patients?
How Many Retrieval Cycles Can Be Done?
There is no fixed number.
Some patients may discuss two retrievals, while others undergo more treatment.
But after every cycle, the key question should be:
Does another retrieval still offer enough expected benefit to justify its time, cost, and treatment burden?
Research on women with poor ovarian response shows that cumulative live-birth probability can increase across repeated cycles, but age and oocyte yield remain major determinants.
The benefit of repeated treatment should not be assumed to rise indefinitely at the same rate.
Can Retrieval Cycles Be Performed Close Together?
Some treatment plans use consecutive stimulation cycles or other strategies designed to obtain oocytes within a shorter period.
Whether this is appropriate depends on:
Previous response
Ovarian status
Menstrual timing
Age
Treatment objectives
Physician assessment
Faster banking is not automatically better banking.
How Does PGT Affect Embryo Banking?
When PGT has a clear clinical indication, embryo number may become relevant to planning.
Not every embryo:
Reaches a stage appropriate for biopsy
Produces a usable test result
Is suitable for transfer after testing
For this reason, the expected number of embryos may sometimes be discussed before genetic testing.
However, PGT itself does not automatically justify embryo banking in every patient.
Read also: IVF With PGT-A and PGT-M in Istanbul
Is Embryo Banking Better for Poor Responders?
Not necessarily.
A retrospective study of poor ovarian responders comparing embryo banking with no banking found lower cumulative live birth in the banking group and a longer time to live birth.
Because the study was observational, it cannot prove that banking itself caused the difference.
However, it is important evidence against assuming that:
more embryos stored before the first transfer automatically means a better final outcome.
Age and Oocyte Yield Matter More Than the Number of Retrievals Alone
Recent data in poor responders continue to show that both age and the number of oocytes retrieved are important predictors of cumulative live birth.
Older age substantially reduces expected success even when several treatment cycles are attempted.
The better question is therefore not:
“How many retrievals can I do?”
but:
“What is the realistic expected value of another retrieval at my age and with my previous response?”
Does Embryo Banking Guarantee a Chromosomally Normal Embryo?
No.
Increasing the embryo number creates more opportunities but does not change the biology of the oocytes.
Five banked embryos do not mean that all five will:
Survive warming
Implant
Produce pregnancy
Lead to live birth
Be chromosomally normal
This distinction becomes increasingly important as female age rises.
What If More Than One Child Is Desired?
This is one of the situations worth discussing early.
A patient hoping for two or more children may wish to consider that oocyte age continues to increase while she completes her first pregnancy and postpartum period.
Some patients therefore discuss additional retrievals before first transfer.
However, this remains an individualized strategy and must be balanced against the opportunity represented by embryos already available.
What If the Second Retrieval Produces No Embryos?
This possibility should be discussed before treatment.
A patient may postpone transfer of an existing embryo hoping to create additional embryos, yet the next retrieval may produce no suitable embryo.
That does not necessarily mean the decision was incorrect.
It simply illustrates why another retrieval should be viewed as:
an additional opportunity—not a guarantee.
How Long Does Embryo Banking Take?
The duration depends on how many retrieval cycles are planned.
Two separate stimulations may extend embryo creation across multiple menstrual cycles, followed by a frozen embryo transfer cycle.
The timeline may become longer when:
Recovery time is needed
Another medical issue needs treatment
PGT is performed
Transfer preparation is postponed
The relevant outcome is therefore not only time to bank embryos, but also time to pregnancy or live birth.
How Does Embryo Banking Affect Cost?
Every additional retrieval can add costs for:
Stimulation medication
Monitoring
Egg retrieval and anesthesia
Fertilization and embryology
Embryo cryopreservation
Storage
Future frozen embryo transfer
Embryo banking can therefore cost substantially more than moving directly to transfer of an available embryo.
The additional expense should be justified by a meaningful treatment objective rather than simply a desire to reach a larger embryo number.
Another Retrieval or Transfer Now?
The discussion can be framed this way:
| Situation | Question to Discuss |
|---|---|
| No usable embryo | Is another retrieval appropriate? |
| One embryo with diminished reserve | Transfer now or bank more first? |
| Several suitable embryos | Is more banking actually necessary? |
| More than one future child desired | Would another retrieval now preserve more future opportunities? |
| Advancing age | Does another retrieval add enough value to justify delaying transfer? |
| PGT for a clear indication | Does expected embryo number affect the testing plan? |
| High financial or treatment burden | Is the expected benefit sufficient? |
When Should Banking Stop and Transfer Begin?
This question should be revisited after every retrieval.
Moving to transfer may become more appropriate when:
Enough embryos are available for the agreed goal.
Another retrieval has limited expected value.
Ovarian response is declining.
Treatment burden or cost is becoming disproportionate.
The patient wishes to begin attempting pregnancy.
There is no medical reason to continue delaying transfer.
Embryo banking should not become an open-ended commitment to repeated retrievals.
Can a Banking Retrieval Be Cancelled?
Yes.
Each stimulation cycle still needs individual monitoring.
If response is unexpectedly poor or a safety issue develops, retrieval may be reconsidered.
Low response alone does not automatically require cancellation, particularly when a low response was expected from the beginning.
Read also: When Is an IVF Cycle Cancelled Before Egg Retrieval? Causes and What Happens Next
Questions to Ask Before Choosing Embryo Banking
Ask:
Why are we delaying transfer of the embryo already available?
What is the objective of another retrieval?
How many oocytes are realistically expected?
How many embryos developed in the previous cycle?
Do we hope for one child or several?
Does age make another retrieval now potentially useful?
What is the realistic chance of obtaining another usable embryo?
Is PGT planned, and why?
How many retrievals will we attempt before reassessing?
What happens if the next retrieval produces no embryo?
How do cost and time compare with transferring now?
Clear answers to these questions are more useful than an arbitrary embryo-number target.
Conclusion
Embryo banking means:
performing multiple egg retrieval cycles and cryopreserving the resulting embryos before beginning embryo transfer.
It may be worth discussing in selected patients with low embryo yield, specific family-building goals, or certain treatment pathways involving embryo testing.
However:
embryo banking is not a treatment for diminished ovarian reserve, does not guarantee success, and has not been shown to be automatically superior to transferring an available embryo in all poor responders.
The most useful question is not:
“How many embryos should I bank?”
It is:
“Will another retrieval now add meaningful value compared with transferring the embryo I already have?”
That decision should balance:
age + existing embryos + previous response + family goals + time + cost + expected benefit of another retrieval
Fertiliv helps patients organize previous retrieval and embryo-development records and coordinate review of whether further embryo banking or moving to transfer is more appropriate.
Frequently Asked Questions: Embryo Banking Before Transfer: When Are Multiple Egg Retrieval Cycles Considered?
What Is Embryo Banking?
It means completing more than one egg retrieval and freezing the embryos produced before beginning embryo transfer.
Is Embryo Banking the Same as Freeze-All?
No. Freeze-all can follow a single retrieval, while embryo banking usually involves multiple retrieval cycles.
Does Every Patient With Diminished Ovarian Reserve Need Embryo Banking?
No. Age, previous response, available embryos, and reproductive goals must all be considered.
Does Banking More Embryos Improve Success?
More embryos provide more transfer opportunities, but delaying all transfers to bank embryos has not been proven superior for every patient.
How Many Embryos Should Be Banked?
There is no universal target. The appropriate plan depends on age, family goals, embryo development, and previous treatment.
Can I Transfer If I Have Only One Embryo?
Yes. One suitable embryo does not automatically mean another retrieval is required first.
How Many Retrieval Cycles Can Be Used for Banking?
There is no fixed number. The expected benefit should be reassessed after each cycle.
Is Embryo Banking Useful If I Want More Than One Child?
It may be worth discussing because oocyte age continues to increase over time, but it is not necessary for every patient.